What is different when the service is care
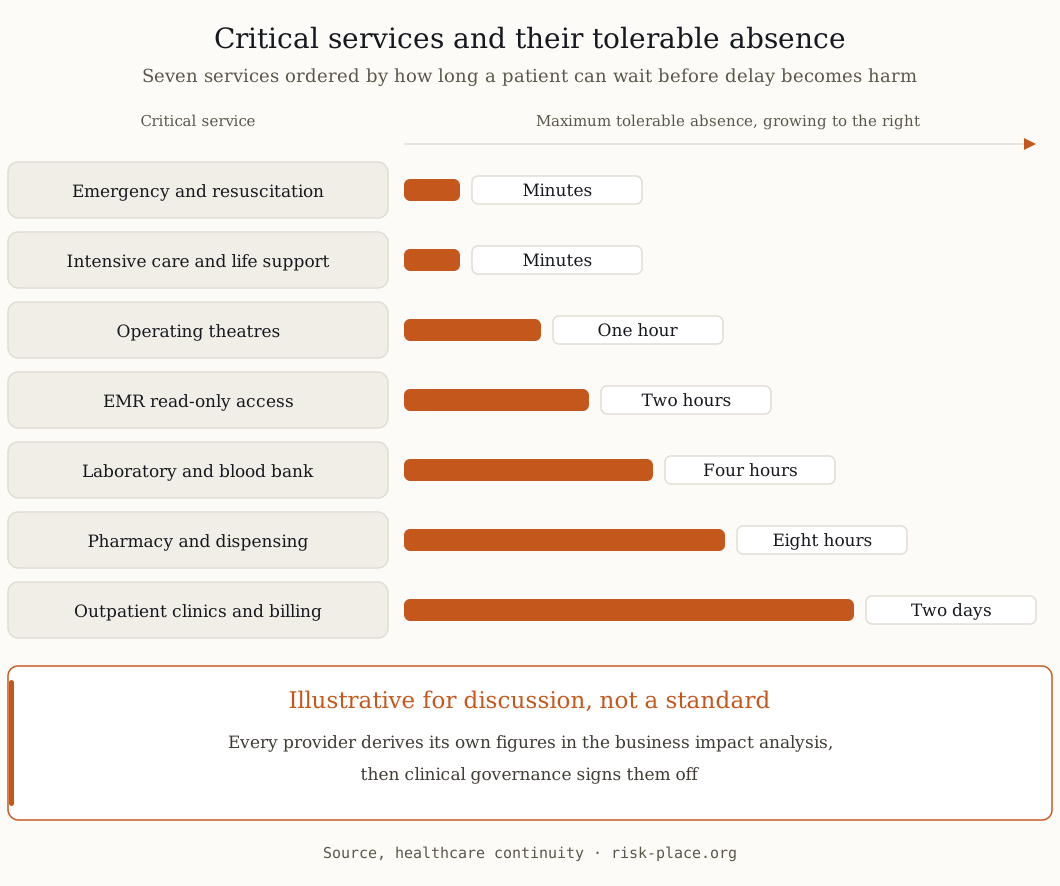
In healthcare, continuity failures convert directly into clinical risk: a delayed result, an unavailable record, a postponed procedure. The BIA therefore ranks activities not only by revenue but by patient-harm potential over time — and recovery objectives are set by clinical tolerance, not commercial preference. That is a higher bar, and regulators, accreditors and insurers all read against it.
The five scenarios that define readiness
| Scenario | The healthcare-specific stakes | The test of readiness |
|---|---|---|
| EMR / HIS downtime | Orders, results, allergies, medication lists inaccessible | Downtime forms and read-only mirrors at ward level; staff trained on the paper path |
| Ransomware | An outage plus a patient-data breach in one event | Segmentation, offline backups tested by restore, a notification path that satisfies UAE data law |
| Utility failure | Power and cooling carry life-support load | Generator autostart tested under load; fuel contracts with delivery SLAs |
| Supply interruption | Pharmaceuticals, consumables, oxygen, blood products | Stock policies per criticality class; alternate suppliers pre-qualified |
| Area incident / access restriction | Staff cannot reach the facility; patients keep arriving | Shift extension protocols, staff accommodation plan, transfer agreements |
The plan, clinical edition
- Ward-level downtime kits. Paper forms, procedures and contact sheets physically present where care happens — a plan on the intranet is unavailable in precisely the scenario it exists for.
- Clinical prioritisation logic. Which services degrade first, which never: decided by clinical governance in advance, so the 2 a.m. decision is an application, not a debate.
- Restore-tested backups. For clinical systems the RPO conversation is about safety; a backup proven only by its existence protects no one.
- Transfer and diversion agreements. Which patients go where when capacity or capability drops — agreed with receiving facilities before the day.
- Communication that keeps trust. Patients, families, staff, regulator, media — pre-drafted, honest, and clinically reviewed.
The sector's hardest lesson, repeated globally: hospitals that rehearse EMR downtime treat it as an inconvenience; hospitals that do not, treat it as an emergency. The difference is a few drills a year.
The UAE regulatory frame
Healthcare operators in the Emirates work under health-authority licensing and inspection regimes, with hospital accreditation standards requiring emergency and continuity management — and public healthcare entities and designated critical facilities fall within the NCEMA 7000 perimeter. Patient data protection under UAE law adds a legal clock to any cyber incident. The practical consequence: continuity evidence in healthcare must satisfy clinical, regulatory and data-protection readers at once.
Hospital business continuity plan: what it contains
A hospital plan is not one document but a thin core plus one card per clinical area. The core holds what is true everywhere; the cards hold what the ward actually does when the screens go dark.
| Part | What is in it | Who writes it |
|---|---|---|
| Core plan | Activation criteria, command structure, communication lines, stand-down rule | Continuity lead with the medical director |
| Clinical area cards | Downtime procedure per ward: forms, identification, medication checks, handover | Each department head |
| Records downtime pack | Paper forms matching the electronic record, printed and in date | Health information management |
| Diversion and surge | When to stop accepting, where patients go, who agrees it with neighbours | Emergency department |
| Supply and utilities | Oxygen, power, water, sterile stock: hold times and refill routes | Facilities and supply chain |
| Recovery and reconciliation | Entering the paper period back into the system without losing care events | Clinical informatics |
Two rules separate a working hospital plan from a binder. Every downtime form must exist on paper tonight, in the version that matches the current system, because a form printed two upgrades ago creates its own incident. And the plan must be rehearsed with the night shift, which is smaller, less senior and the one most likely to meet the outage first.
Frequently asked questions
Where should a clinic with limited resources start?
EMR downtime procedures at the point of care, restore-tested backups, and the utility check — generator, fuel, cooling. Those three cover the incidents that actually occur, and all fit within weeks.
How often should downtime procedures be drilled?
At least annually for the full scenario, plus short ward-level refreshers each quarter — new staff join continuously, and the paper path only works if the newest nurse on the shift knows it.
Does ISO 22301 apply to hospitals?
Yes — and it maps well onto accreditation requirements. For UAE providers the pragmatic route is one continuity system designed against clinical risk, documented to satisfy accreditor, regulator and — where applicable — NCEMA logic together.